


I gave my cardiologist a heart attack. Well—not literally.
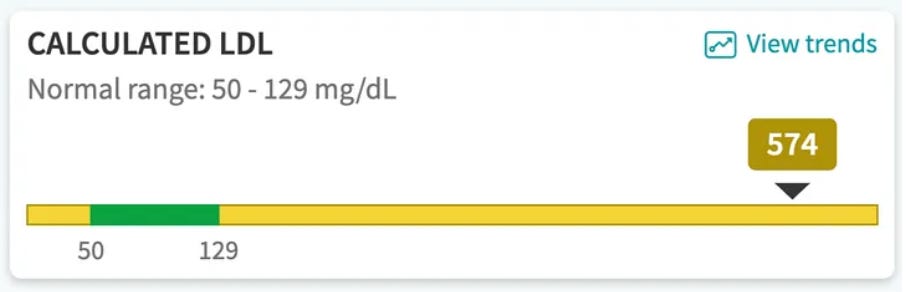
But when a cardiologist sees an LDL cholesterol of 574 mg/dL, their eyes bug out like they’re a human-sized fruit fly.
And I understand why.
That number is higher than anything most doctors have seen in their entire careers. And it’s scary. It is.
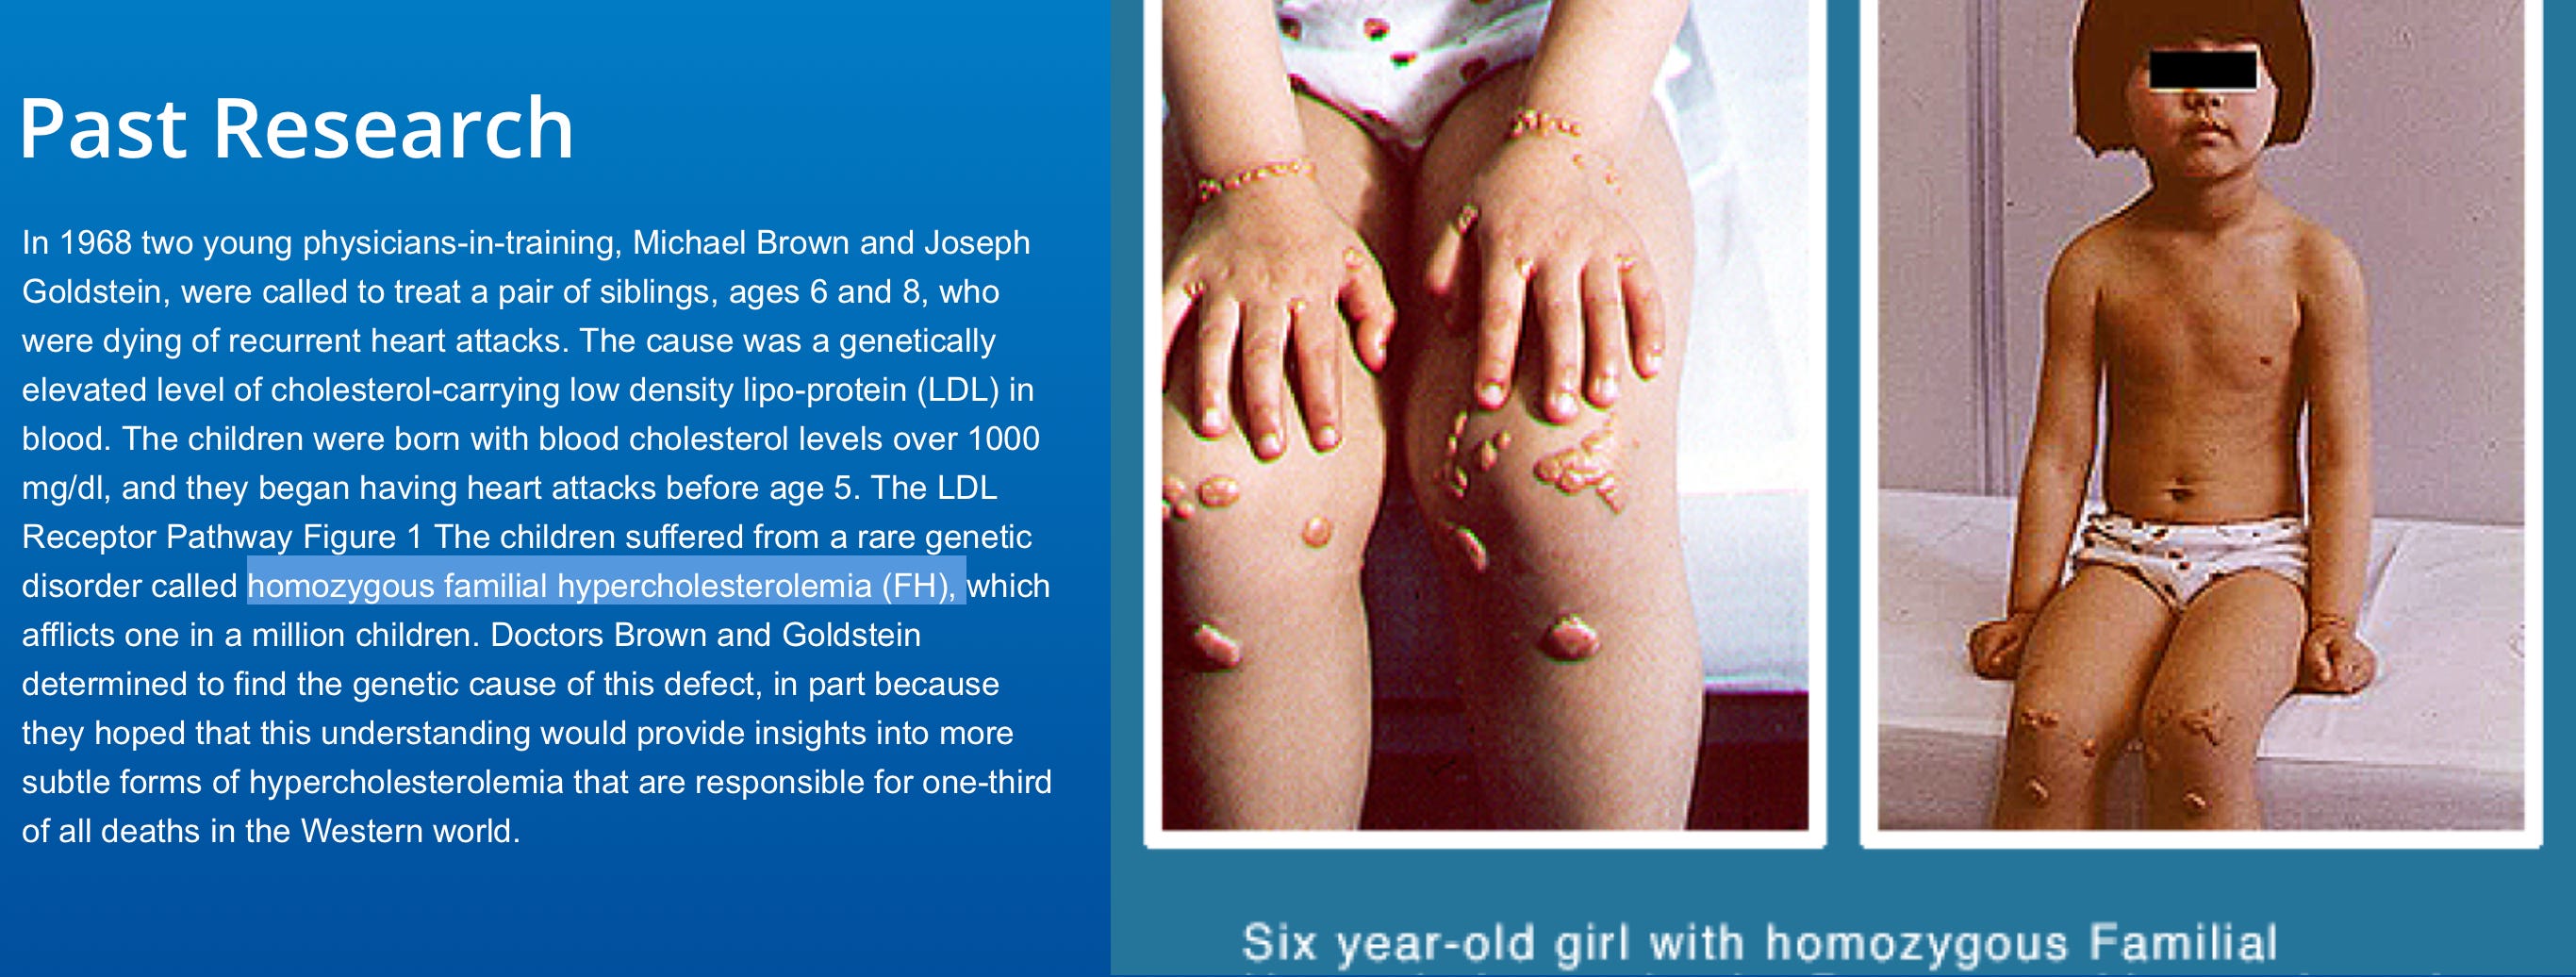
It rivals levels found in “homozygous familial hypercholesterolemia,” a rare genetic disorder—occurring in ~1 in a million—that can cause fatal heart attacks in children as young as eight.
But I don’t have familial hypercholesterolemia.
Something very different is going on inside my body…
But let me first, acknowledge that the fear of LDL cholesterol (LDL-C)—and more specifically, ApoB-containing lipoprotein particles—is cemented into the bedrock of modern cardiology.
This isn’t a criticism per se; it’s a recognition of the prevailing model.
But, once my doctors recover from their (metaphorical) surprise-induced myocardial infarction, their fear turns to confusion.
How could a Harvard–Oxford-trained MD-PhD be walking around with an LDL of 574 mg/dl, unmedicated?
I once had someone tell me, “I feel as if I just saw Einstein snorting lines in a flat-Earther T-shirt.”
I guess that’s a compliment?
And then confusion turns to disbelief when I explain that not only do I understand how to lower it—I could drop it to 90 mg/dl within a couple of weeks. All I’d have to do is add carbohydrates back into my diet.
My LDL-C is elevated not because of a genetic defect (I do not have familial hypercholesterolemia) but because I am on a ketogenic diet AND I’m lean.
*Nick Note: I am not on a ketogenic diet to lose body fat or for performance but because it’s therapeutically necessary to keep my ulcerative colitis in remission.
The Lean Mass Hyper-Responder & Why It Matters
This is a known phenomenon: lean individuals on ketogenic diets often see dramatic increases in LDL-C.
To be clear, this is not the majority response to carbohydrate restriction and ketogenic diets.
Most people who go low-carb experience no change or decreases in LDL-C and ApoB because most people who adopt low-carbohydrate diets are overweight or obese.
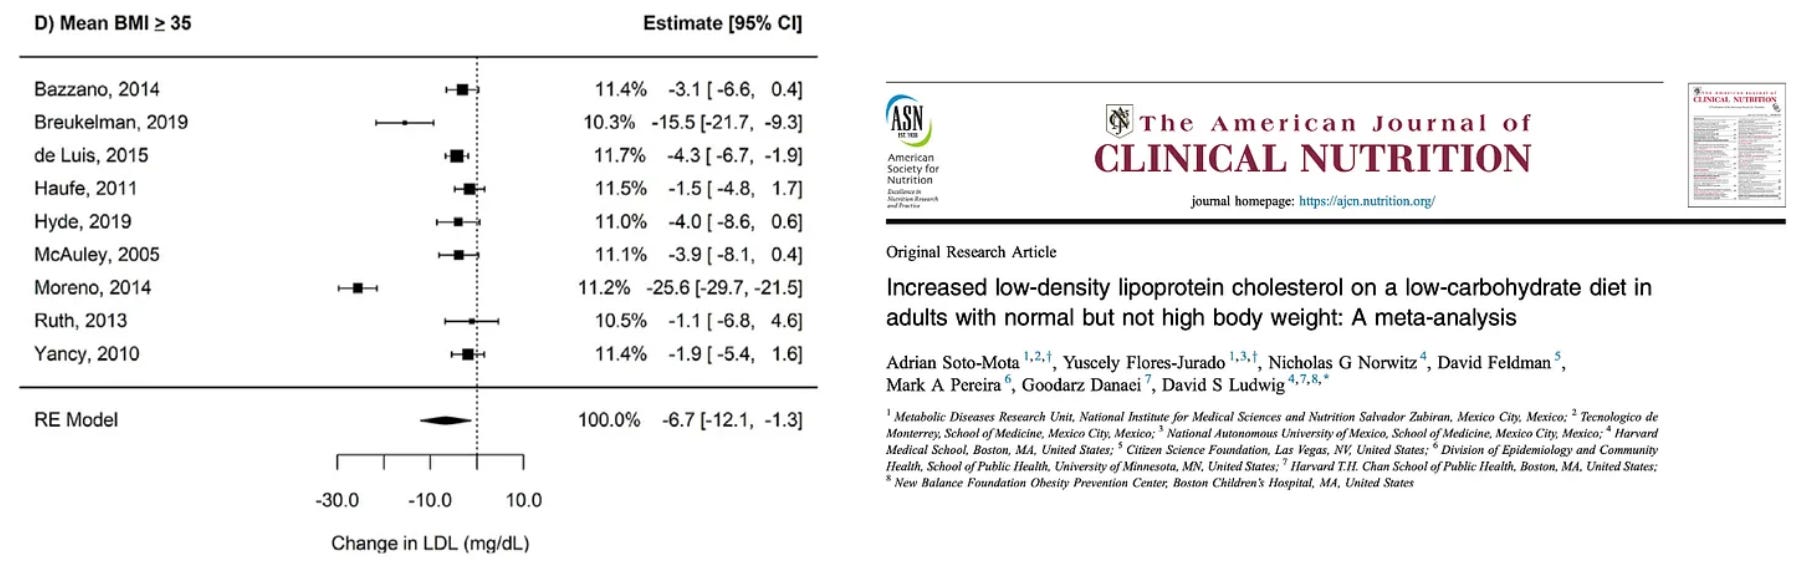
*Forest plot from a meta-analysis of randomized controlled trials showing that for persons with class II obesity, LDL cholesterol tends to decrease on carbohydrate-restricted diets.
But among lean, insulin-sensitive individuals on low-carbohydrate diets, LDL-C and ApoB can rise—sometimes astronomically.
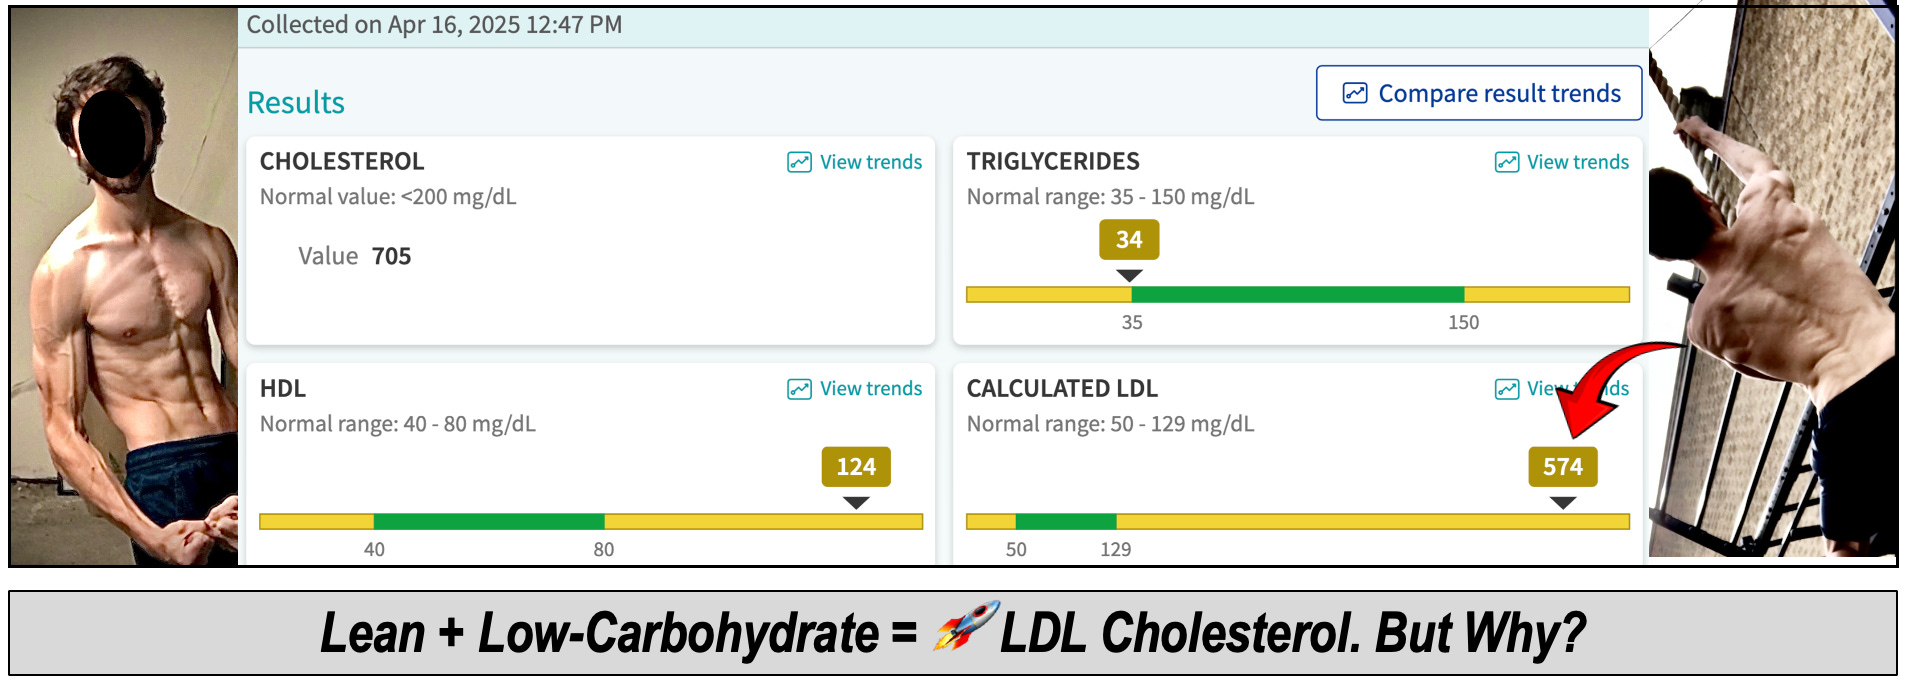
This response is now recognized as a distinct metabolic phenotype known as the Lean Mass Hyper-Responder (LMHR).
My colleagues and I have been studying LMHR for years—trying to understand what they are, why they respond this way, and what their true risk profile might be.
And yes—as many of you know—this research has become a lightning rod for controversy on social media.
A Roadmap
In the remainder of this letter, I’m going to pull back the curtain. I’m going to
To explain the LMHR are, including their what, why, and how.
To clarify my personal position and choice to walking around with an LDL of 574 mg/dl Specifically, I’ll discuss:
The Naturalistic Fallacy
Potential Benefits of Treatment
Potential Risk of Treatment
A Tricky Risk-Benefit Analysis
My Cardiac Imaging and What it Means
I will also disclosure What I’m Trying Next for my LDL, and why.
To direct you to many more learning resources.
*Of course, none of this is medical advice. This is NOT a ‘do as I do’ but rather a ‘see as I think’ so you can approach your N = 1 with careful control.
Defining the Lean Mass Hyper-Responder (LMHR)
LMHRs are individuals who adopt a low-carbohydrate diet and experience a triad of lipid markers: LDL ≥ 200 mg/dL, HDL ≥ 80 mg/dL, and triglycerides ≤ 70 mg/dL. This lipid profile is rare in the general population but surprisingly common among lean individuals who go low-carb.
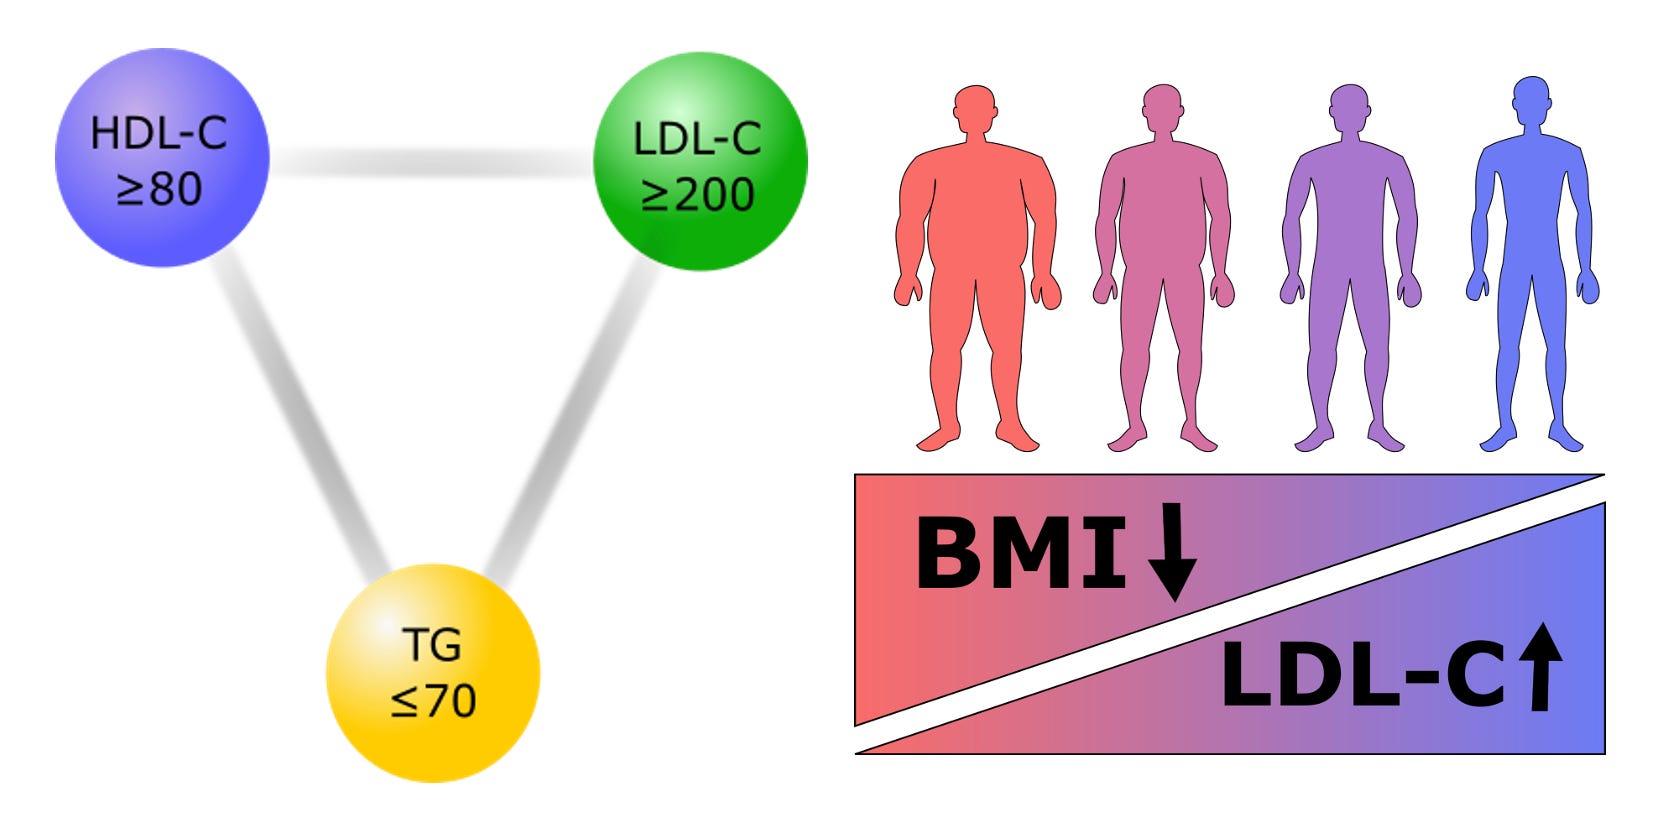
To be clear, being “lean” is not actually a criterion.
Technically, you could have a BMI of 50 kg/m2 and be a LMHR. Although I don’t think such a person exists.
The term “lean mass,” in lean mass hyper-responder reflects a hypothesis: that this pattern emerges particularly in those who are lean, insulin-sensitive, and carbohydrate-restricted.
It’s not a fixed rule, but a metabolic fingerprint.
And importantly, this must be distinguished from familial hypercholesterolemia, where LDL-C and ApoB levels are high from birth due to a genetic defect in lipid metabolism.
In contrast, LMHRs generally have normal cholesterol on mixed diets, and see their LDL-C surge only when they restrict carbs. This can on any diet from a carnivore diet to a vegan ketogenic diet.
As a point of emphasis, the LMHR phenotype is neither the result excess saturated fat or a ‘fiber deficiency’ — LMHR are far more interesting.
And physiologically, it makes sense…
Lipid Energy Model
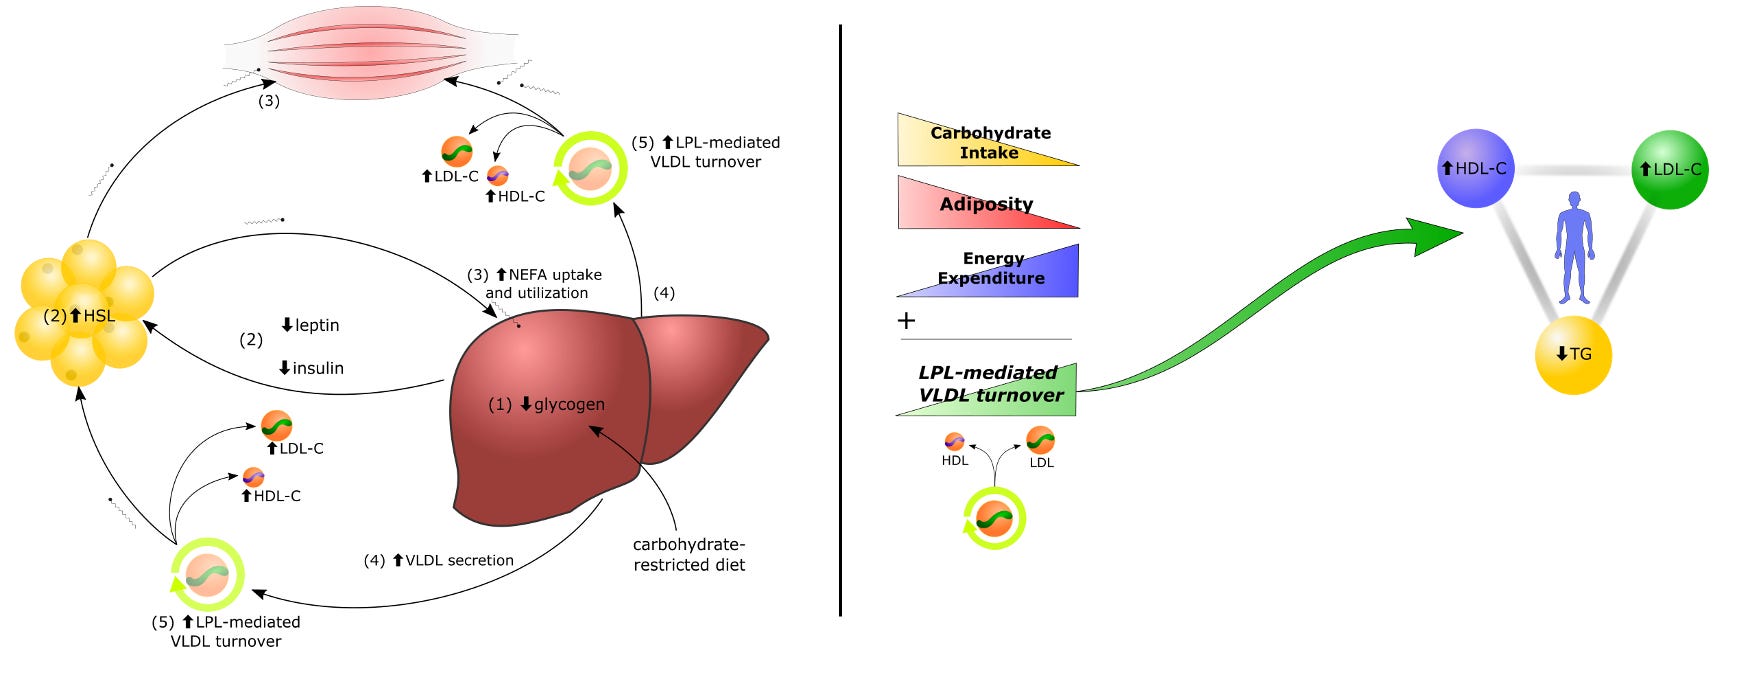
The Lipid Energy Model, which explains the LMHR phenotype (and was first put forth by my friend and colleague Dave Feldman), proposes that when you’re lean and insulin-sensitive, going low-carb increases fat mobilization (1-2).
Free fatty acids are released into the bloodstream and taken up by the liver (3), where they’re repackaged into VLDL particles (4), precursors to LDL particles.
These VLDLs don’t build up because they’re rapidly offloaded to muscle and fat tissue for energy. Otherwise stated, there is “rapid VLDL turnover” (5), which produces LDL particles, elevates HDL-C, and lowers triglycerides.
Simply increasing my physical activity—say, just walking more—can raise my LDL-C by 50 mg/dL.
While the Lipid Energy Model is still a hypothesis, it continues to predict outcomes remarkably well. It’s the best working model we have.
So, Why Just in Lean People?
But you might ask: Why does this mainly happen to lean people?
Why not in those with obesity? We don’t fully know.
But we do know:
Lean Body, Fast Fat Shift
Lean, insulin-sensitive individuals tend to ramp up fat metabolism more effectively when restricting carbs.
Fat is an Endocrine Organ
Fat releases hormones like leptin, adiponectin, 12,13-diHOME, MPO, and others that shift metabolic dynamics. These hormones likely influence whether someone becomes an LMHR.
I’d also add that everyone also has a different “personal fat threshold.” For some, LMHR traits show up below a BMI of 27 kg/m2; for others, below 22 kg/m2. Some people may never become LMHRs, no matter how lean they get. So, while this is not a primary genetic condition, there may be “permissive” or “restrictive” genetics.
Inverse Relationship: BMI vs LDL Change on Low-Carb Diets
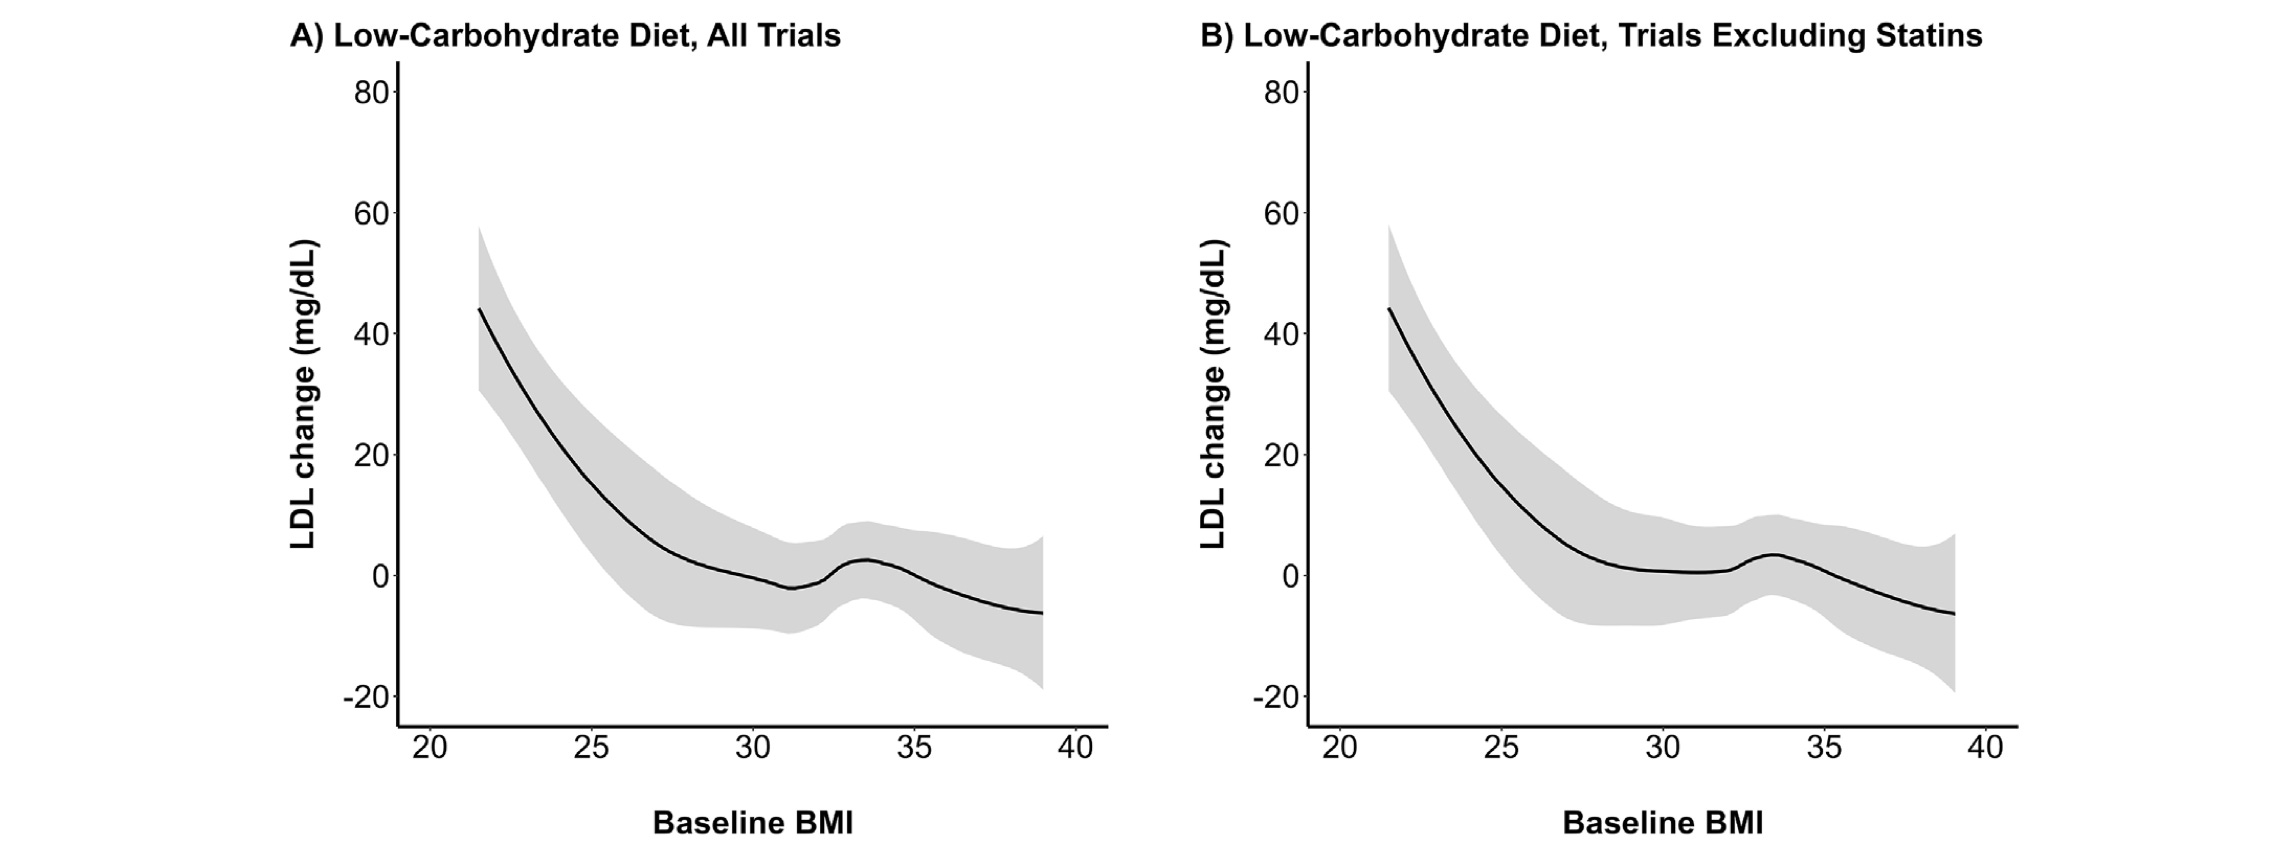
Additionally, we have strong evidence for this inverse relationship between LDL-C change and BMI, consistent with the Lipid Energy Model.
We’ve even published a meta-analysis of 41 randomized controlled trials showing that the leaner you are, the greater your LDL-C increase on a low-carb diet.
The Cholesterol Hairpin Turn Phenomenon
Clinicians are seeing it too: many patients’ LDL-C stays flat or declines as they lose weight on ketogenic diets—until they reach a BMI under ~25 kg/m2.
Then it spikes sharply!
There are numerous examples, but here is one that I have permission to share:
My colleague, Dr Professor Adrian Soto Mota MD PhD, cared for a 60 year-old male patient with type 2 diabetes. The patient adopted a ketogenic diet and his BMI steadily decreased from 29.5 kg/m2 to 24.5g/m2. During his weight loss journey, his LDL-C remained ~95 mg/dl until he reached the “healthy” BMI range (< 25 kg/m2). Then, his LDL-C jumped to 183 mg/dl.

So now, the bigger questions begin:
Are Lean Mass Hyper-Responders truly at elevated cardiovascular risk?
And why am I— a conventionally trained, MD/PhD — walking around with an LDL-C in the 500s... completely unmedicated? Am I crazy, or thoughtful?
In the remainder of this letter, I dive deep into these provocative questions — and much more:
Are Lean Mass Hyper-Responders at High Cardiovascular Risk?
Where is the actual evidence — and What’s Coming Next?
My LDL-C is 574. Why am I still unmedicated?
What I’m going to try next (upcoming N= 1 experiment)
Caution! Don’t fall for the Naturalistic Fallacy
My specific concerns with lipid-lowering drugs (Statins, PCSK9 inhibitors)
How I personally weigh the risks and benefits
Extra learning resources: KETO-CTA, Lp(a), heart-focused nutrients, and more
Admittedly, this letter is a bit of a beast. But for those who really care about nuance, metabolic context, and learning how to be an independent thinker and grapple with unknowns, take the leap. It will be worth it.
